
If you have noticed difficulty in passing urine, a painful stream or a thin stream, have urination that stays you up at night, or have that urinating feeling without feeling as though you completely empty the bladder, then this could be a urethral stricture. This condition could be restraining the function of one of the most necessary bodily functions and is one of the most underdiagnosed diseases. This is mainly due to the feeling of embarrassment that most men feel while deciding to seek help.
Urethral stricture provides a lot of that good sustenance and is fully treatable. Especially in Indore, treatments are provided at a city-level metro without the requirement of traveling there.
Dr. Vikas Singh, Senior Consultant Urologist at Kokilaben Dhirubhai Ambani Hospital, Nipania, Indore, has one of the most reconstructive urologists in Central India. He has a lot to offer when in view of urethral stricture treatments. His services include the most advanced Buccal Cell Implant techniques, Open Urethroplasty, and a variety of minimally invasive Laser OIU services. The best treatment is provided by a dedicated team that takes an ample amount of time to understand each patient’s lifestyle goals and aspirations.
If you have lived with this condition in the long term and have been continuously looking for options, then you may have just contacted the right place. We can promise you that you will be extremely satisfied.
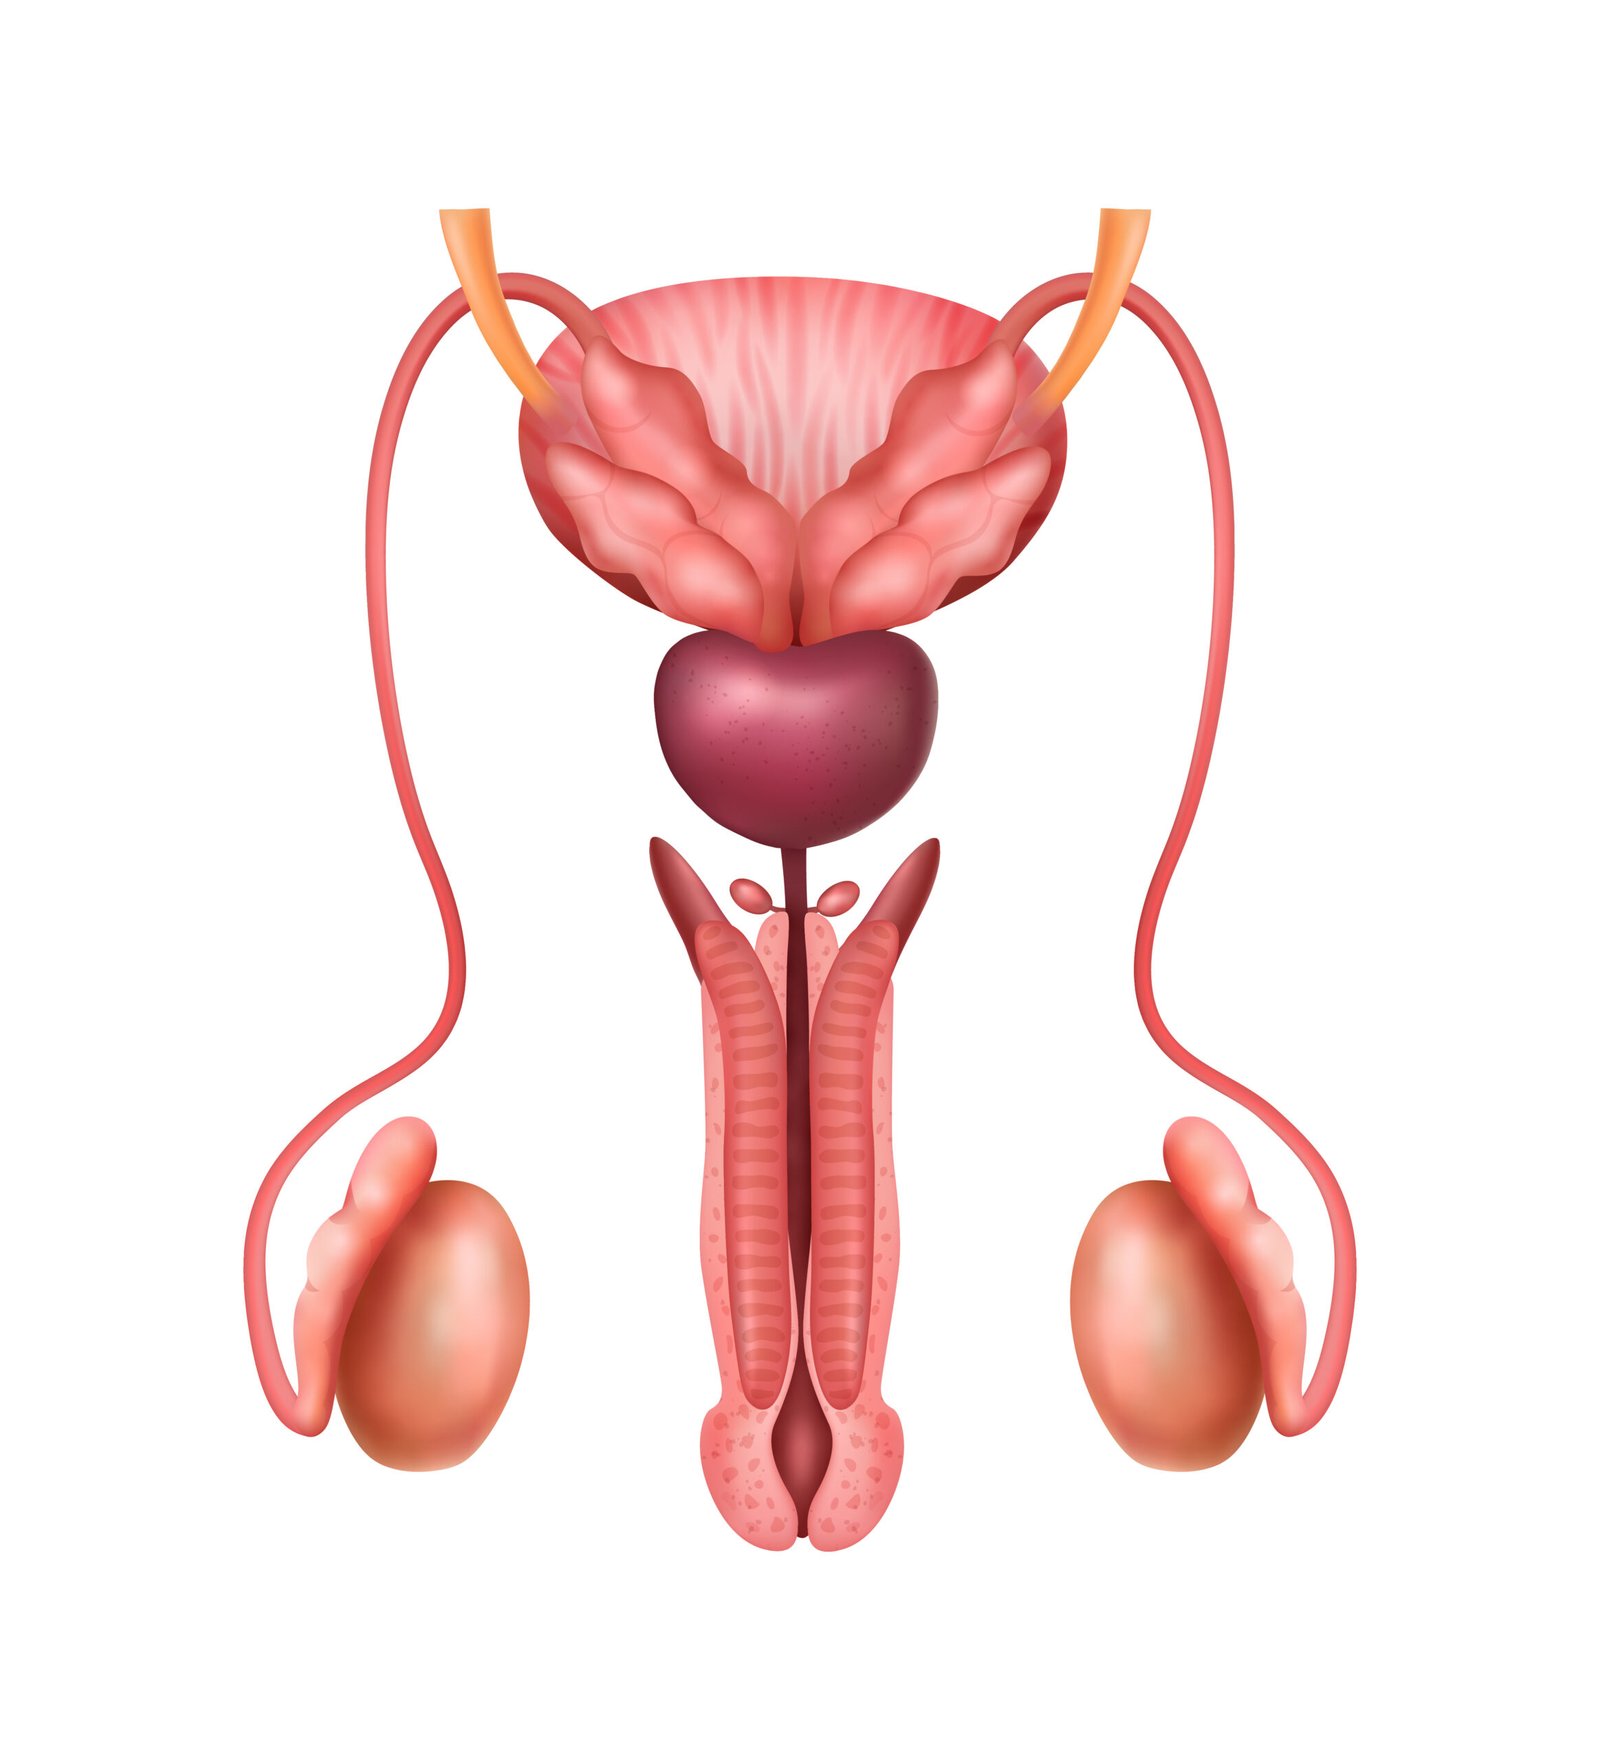
The urethra is the tube that carries urine out of the body, running through the prostate and penis in men, and just below the bladder in women. When it becomes injured, infected, or inflamed, scar tissue can form and narrow the passage, much like a kink in a garden hose slowing water flow.
This narrowing makes it harder for urine to pass, forcing the bladder to work harder. Over time, this can damage the bladder and cause urine to back up into the kidneys, leading to infections and further damage.
While it’s more common in men and can happen at any age, from younger men after pelvic injuries to older men following prostate surgery or catheter use, it’s often mistaken for an enlarged prostate, making expert evaluation important. Urethral strictures also tend to recur once scar tissue forms, so choosing the right treatment and an experienced surgeon makes a real difference in long-term results.
Urethral strictures develop when scar tissue forms in the lining or surrounding layers of the urethra. The reasons this happens vary widely from patient to patient.
Here are the most common causes:
Physical trauma, especially in younger men, is a common cause. A straddle injury, like falling onto a bicycle bar, can crush the urethra and lead to scarring as it heals. Pelvic fractures from accidents can also tear the urethra near the bladder, causing a complex condition called PFUDD. Dr. Vikas Singh has experience treating even these difficult cases through reconstructive urethroplasty.
Sexually transmitted infections, especially gonorrhea, have long been a major cause of urethral stricture worldwide, as repeated or poorly treated infections can scar large portions of the urethra. Recurrent UTIs can also cause localized inflammation. Lichen sclerosus, a chronic skin condition affecting uncircumcised men, is another stubborn cause that tends to spread and recur even after treatment.
Strictures often develop after medical procedures, including:
In a small number of cases, urethral stricture can be congenital – meaning present from birth due to abnormal development of the urethra during foetal development. Congenital strictures are more commonly associated with other urological anomalies. They may not cause significant symptoms until the child grows older or until they are discovered during the investigation of other urinary problems.
Many men mistake these symptoms for normal aging or prostate issues and ignore them for months or years, but the longer they go untreated, the more scar tissue builds up, making treatment harder. Watch for:
Diagnosis helps establish the foundation of treatment. In order for a patient to receive the most optimal treatment available for their case of urethral stricture, Dr. Singh takes a multi-faceted approach by integrating all functional assessments, imaging studies, and direct visual assessments of a patient’s urethral stricture at Kokilaben Hospital, Indore. This provides the extent, length, and characteristics of the stricture, as well as and other related scarring.
Uroflowmetry And Diagnosing Urethral Strictures
Uroflowmetry is a simple, non-invasive test that measures how fast and how much urine you pass, done by urinating into a special measuring funnel. A healthy flow is usually above 15ml/sec, while a stricture often drops this below 10ml/sec. Dr. Singh uses this test to gauge the severity of blockage and track improvement after treatment. It’s often paired with a post-void residual check, if more than 100ml of urine remains in the bladder, it suggests incomplete emptying.
Retrograde Urethrogram (RGU)
RGU is the gold standard imaging test for urethral strictures. A contrast dye is injected into the urethra, and X-rays capture the connection between the urethra and bladder. This helps pinpoint the exact location and shape of the stricture, key information for planning surgery. In some complex posterior strictures, a Micturating Cystourethrogram (MCU) may also be used.
Cystoscopy
A thin, flexible camera is passed through the urethra to directly view the stricture and check for related bladder changes, like stones or thickening. It’s usually done under local anesthetic gel as an outpatient procedure. In cases of severe blockage, the scope may not pass through, which itself gives useful diagnostic information.
Ultrasound and Imaging
Urethral ultrasound checks the length of the stricture and the extent of scarring (spongiofibrosis) without using radiation, more scarring often means a more complex case. A kidney and bladder ultrasound checks for related complications, while a pelvic MRI helps map out complex strictures, especially after pelvic fractures, aiding surgical planning.
Urethral Stricture Treatment Options Available in Indore
Treatment depends on the stricture’s length, location, whether it’s new or recurring, and the patient’s overall health. Dr. Vikas Singh offers the full range of treatment options, from simple to advanced, at Kokilaben Hospital Indore.
Collagen (Urethra) Implants
Surgical Reconstruction of the Urethra, or Urethroplasty for short, is the most proven of urethra stricture surgical treatments, as well as being the most successful. Comparing OIU to Urethroplasty, OIU would probably be considered the least complex, and for the patient who desires the urethra stricture to be treated in his or her long, complex, and recurring stricture, Urethroplasty would be considered the most complex.
OIU and/or Laser OIU
Optical Internal Urethrotomy (OIU) is a quick, same-day procedure using a small blade or laser through a cystoscope to open up the stricture. Laser OIU offers more precision and less tissue damage than the traditional method. It works best for:
That said, recurrence is common, long-term success for anything beyond short, first-time strictures is only 30-50%, with many returning within 1-3 years. Dr. Vikas Singh is upfront with every patient about this limitation.
Recovery typically involves a 3-5 day hospital stay, a catheter for 3-4 weeks, and a return to normal activity within 4-6 weeks. Long-term success with buccal mucosa urethroplasty at experienced centers ranges from 85-92%.
AALBEC is a cutting-edge treatment for urethral strictures, and Dr. Vikas Singh is among the few surgeons in India offering it. The technique combines minimally invasive endoscopy with regenerative medicine, using live cells grown from a small sample of the patient’s own cheek tissue. After a standard OIU procedure opens the stricture, these cells are placed at the site endoscopically, where they help regenerate healthy tissue and reduce the chances of the stricture returning.
Key advantages include:
AALBEC is especially useful for patients with primary or recurrent bulbar strictures, or those for whom open surgery carries higher risk. Studies comparing it to OIU alone show better outcomes in flow rates and symptom improvement. Dr. Vikas Singh will assess your specific case, factoring in stricture length, location, and treatment history, to determine if AALBEC is right for you.
Dilatation is one of the oldest treatments for urethral stricture, involving gradually widening the urethra using instruments of increasing size. While it offers quick, short-term relief, it doesn’t address the underlying cause, and repeated dilatation can actually worsen the scarring over time, making the stricture more severe.
Because of this, dilatation is generally used carefully and only in specific situations:
Great care should be taken when deciding on the treatment option for urethral stricture. The table below provides a rough guide for you to compare the options – however the ultimate recommendation will be made after a personal assessment with Dr. Vikas Singh and consideration of your overall clinical scenario.
| Factor | OIU / Laser OIU | Urethroplasty | AALBEC |
|---|---|---|---|
| Best For | Short (<2 cm), primary bulbar strictures | Long, complex, or recurrent strictures | Primary/first-recurrence bulbar strictures, avoiding open surgery |
| Procedure Type | Endoscopic – no incision | Open surgery – perineal incision | Endoscopic – no incision |
| Success Rate | 30–50% long-term (recurrence is common) | 85–92% long-term (most durable) | Promising medium-term; ongoing research |
| Hospital Stay | 1–2 days | 3–5 days | 1–2 days |
| Recovery Time | 1–2 weeks | 4–6 weeks | 1–2 weeks |
| Catheter Duration | 2–5 days post-op | 3–4 weeks post-op | 5–7 days post-op |
| Recurrence Risk | High (especially if stricture is long or recurrent) | Low (especially anastomotic repair) | Lower than OIU alone; data emerging |
Every patient should understand the consequences following the surgery. For your reference, this is a simplified step-by-step recuperation process for planned procedures:
Urinary catheters post surgery are expected to be in place for an approximate threshold of 3 to 5 weeks. Promotion of light work resumption is expected in a 6 to 8 week fn. avoid sexual intercourse for the same duration.
Urinary catheters are expected to be removed post 3 to 5 days. 3 to 5 days is the threshold for urinary comfort post surgery, and 2 to 5 day are the limits for hospital stays. Promotion of light work resumption is expected in a 3 to 5 day timeframe. 2 to 4 week post-operative care recommendations include the avoidance of strenuous/work related activities, as well sexual intercourse. Uroflowmetry is to be done within 3 to 6 month post procedure.
Urinary catheters are post surgery are expected to be in place for a 3 to 5 day time threshold. 1 to 2 weeks for the resumption of light work. Uroflowmetry and cell engraftment are to be expected to be test ed at 3 to 6 month intervals post surgery
Yes, recurrence is common, especially after endoscopic procedures like OIU, since the underlying scarring tendency isn’t fully resolved. However, the right follow-up care and lifestyle habits can significantly lower the risk.
Regular uroflowmetry helps catch early, silent narrowing before symptoms return
Don’t ignore a weakening stream or returning symptoms, early treatment beats dealing with full recurrence
Untreated infections can contribute to new scarring
STIs like gonorrhea can cause strictures, so prompt treatment and safe practices matter
Let hospital staff know about your stricture so it’s handled by an experienced specialist
If advised after surgery, this helps maintain healing and prevent renarrowing
Proper dermatological care is key if this condition is contributing to your stricture
Urethral strictures -especially those with complications including complexity, recurrency, and those that result from trauma- present a challenging reconstruction problem. Dr. Singh’s Urology specialization blends technical prowess and clinical acumen that makes him an excellent surgeon. Below are the reasons that make Dr. Singh an excellent Urology practitioner:
Dr. Vikas Singh offers a full horizon of surgical options from advanced AALBEC Buccal Cell Implant Techniques to both Laser OIU and multiple forms of urethroplasty. Coupled with the expertise of surgical medicinal avenues, there are very few Urology practitioners in Central India that are able to provide such a breadth of surgical options.
AALBEC is one of the innovative avenues in the endoscopic management of urethral strictures in India and Dr. Vikas Singh is one of the few practitioners that have adopted the method, which caters to the Indore population with access to the lesser available options in the Central India regenerative Urethral Reconstruction arena
Dr. Vikas Singh explains all procedures and covers the success of the procedure and the expected result timelines. On the trade-off, there is no rush in the making. Each patients covers and becomes an integral part of the plan making for the process of the consultancy
Kokilaben Dhirubhai Ambani Hospital Nipania, Indore, has well-provisioned endoscopy suites, modern operating theatres, and exceptional post-operative suites—all required to facilitate the safe and effective conduct of urethral reconstructive surgeries.
Urethral Stricture poses highly sensitive issues. Dr. Vikas Singh and associates strive to offer patients and their caregivers a strictly private, polite, and non-discriminative ambiance.
Posted on GoogleTrustindex verifies that the original source of the review is Google. Dr vikas singh is best urologist in IndorePosted on GoogleTrustindex verifies that the original source of the review is Google. Nice treatmentPosted on GoogleTrustindex verifies that the original source of the review is Google. My treatment given by Dr vikas sir he is best doctorPosted on GoogleTrustindex verifies that the original source of the review is Google. Best doctorPosted on GoogleTrustindex verifies that the original source of the review is Google. Hm log shivpuri se dr vikas sir ko dikhane aaye, sir se milkar bahut acha lga, nature or treatment bahut sahi hePosted on GoogleTrustindex verifies that the original source of the review is Google. Nice doctorPosted on GoogleTrustindex verifies that the original source of the review is Google. Very experienced and caring doctor. Excellent treatment and patient-friendly approach. Highly recommended.”Posted on GoogleTrustindex verifies that the original source of the review is Google. On dt27.06.2026 dr.vikas singh performed my prostatomegaly surgery by Urolift method . I am now fealing very well.Within two days l got discharged from Kokilaban Dhirubhai Ambani hospital Indore (MP).I am very thankfull to this very new method Urolift,Dr.Vikas singh sir and BCM Kokilaben Dhirubhai Ambani hospital,Nipania Indore. ByAdarsh kumar pauranik.Posted on GoogleTrustindex verifies that the original source of the review is Google. Good experience for testis treatment for my son
Yes, urethral strictures can be cured. This condition can be permanently resolved on the condition of the deployment of effective and appropriate surgical intervention. Currently, Urethroplasty, and more specifically, anastomotic urethroplasty for short strictures, has a surgical success rate of more than 90%. Even with longer and more complex strictures, a buccal mucosa graft urethroplasty, can be successful and has positive outcomes with the majority of patients. The secret is to use the best surgical solution for the best surgical stricture.
Whether you are having an OIU, AALBEC, or urethroplasty, Urethral stricture surgery is done under anaesthesia. As a result, during the surgery, you will be unaware. After the surgery, many patients experience pain that is rated as mild to moderate for a short period of time, and is easily treated with the normal analgesics that are available. In terms of recovery, OIU takes about 1 to 2 weeks, while urethroplasty can take 4 to 6 weeks and is still a longer recovery process. However, in general, most patients, are of the opinion that the process is much more bearable than they anticipated.
Urethral stricture surgery is not permanent, and more importantly, it very rarely makes sexual function more difficult. There is little to no impact to sexual function while performing the Laser OIU and AALBEC. There is a slight risk of temporary erectile dysfunction with posterior or complex urethroplasty near the prostate. However, this process does improve with time. Dr. Vikas Singh will explain the specific risks for your case during the consultation and will use nerve-sparing methods whenever possible.
It primarily depends on the location, length, and the patient history involved. For the most part, short primary bulbar strictures can be managed with adjunctive AALBEC or OIU. Complex, recurrent, or long strictures should be managed with urethroplasty for long-term solutions. Dr. Vikas Singh will be able to provide personalized recommendations once the findings of your urethrogram, cystoscopy, and uroflowmetry have been assessed.
For short strictures, anastomotic urethroplasty (the end-to-end type) has a 90% success rate and can be considered good at the long-term outcome. For the extended strictures, the successional rate for buccal mucosa graft urethroplasty is often cited between 5.8 and 9.2 and is most commonly observed at the fifth year for those medical facilities where skilled practitioners can be found. This is a vast improvement over the outcomes most strictures achieve with OIU.
AALBEC (Autologous Adult Live Cultured Buccal Epithelial Cells) is a newer, more modern endoscopic method that requires the use of the patient’s own live buccal cells, which are obtained from the inner lining of the cheek, indirectly processed, and subsequently placed at the site of the urethrotomy after the Laser OIU. This is aimed at stimulating the site to produce the proper structural support overgrowth of tissue, which moderates the effects of stricture. Indore has AALBEC, and it can be performed by Dr. Vikas Singh at Kokilaben Dhirubhai Ambani Hospital. For those patients who are ideal for the procedure and wish to avoid an open surgical procedure, it is one of the most advanced procedure options.
The catheter after Laser OIU is left in about 2-5 days, 5-7 days after AALBEC, and up to about a month after urethroplasty. This is to help heal the urethra after the surgery, as the catheter must remain in the body during the healing process. Existing patients can ask Dr. Vikas Singh at the beginning of the surgery to further explain durations of catheter use.
Yes, but unlike OIU, urethral stricture after a urethroplasty is significantly less common. For strictures that require short strictures, the recurrence rate is less than 10%. For strictures that require a buccal mucosa graft urethroplasty, the recurrence rate at about 5 years is between 8 to 15%. If recurrence of the strictures does occur, regular check-ups with uroflowmetry will help identify them the fastest and will allow the fastest action to be taken.
Yes, but it is very rare for women to be diagnosed with strictures than it is for men. Women with urethral strictures may have weak urinary tract flow, painful urges to urinate, and may have a lot of urinary tract infections. This can be a result of surgery done to the pelvis, trauma caused to the urinary tract by a catheter, burns, and radiation. An example of the surgery is a confronted buccal mucosa graft urethroplasty that is done on females with urethral strictures. Dr. Vikas Singh. does address and help with females with urethral strictures as well.
Call at +91 81468 73931 or go to Kokilaben Dhirubhai Ambani Hospital, No. 1, BCM Estate, Nipania, Indore, Madhya Pradesh 452010. Please provide the previous investigation reports and show the videos on uroflowmetry, images of the urethrogram, or reports of the cystoscopy. If you underwent urethral stricture surgery in the past, the reports regarding the previous surgery are valuable in designing the optimal approach to your surgery.